
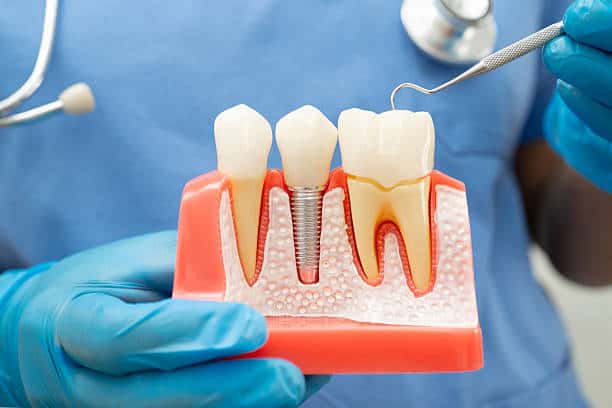
Many patients believe that once a dental implant has fused with the jawbone, the biological story is over. That fusion process, known as osseointegration, is a major milestone. But it is not the end point.
Jawbone is living tissue. It stays metabolically active for life, responding to chewing forces, general health, and daily wear long after surgery is finished. This ongoing process is called bone remodeling, and it plays a direct role in dental implant durability.
After osseointegration, every bite introduces mechanical loading to the bone around the implant. Cells called osteoblasts build new bone. Cells called osteoclasts remove older or damaged bone. Together, they keep the jawbone adapting to the demands placed on it.
Healthy bone remodeling is one of the quiet factors behind long-term implant success. Understanding how it works helps patients considering dental implant treatment know what to expect well beyond the healing period, and it helps current implant patients understand why implant stability depends on more than the initial surgery.
Bone remodeling is the coordinated process by which the body continuously removes older bone tissue and replaces it with new bone. It is not unique to dental implants. This same cycle happens around natural teeth and throughout the skeleton for a person’s entire life.
Around a dental implant, remodeling allows the surrounding bone to adjust to the presence of a titanium root and to the forces that come with normal chewing.
Osteoclasts are specialized cells that break down and clear away bone tissue that is old, damaged, or no longer needed in its current form. This process, called resorption, sounds like something to avoid, but it is a normal and necessary part of healthy bone biology. Without it, bone could not renew itself or adapt to changing demands.
Osteoblasts follow behind osteoclast activity, forming new bone tissue in the spaces that resorption creates. This new bone matures over time, gradually gaining strength and density. Around a dental implant, this is part of how the surrounding bone continues to support the implant well past the initial healing period.
The relationship between resorption and formation is what determines long-term outcomes. When these two processes stay roughly balanced, the bone around an implant remains stable. When resorption consistently outpaces formation, the supporting bone can gradually weaken, which may eventually affect implant stability. That balance, not the absence of any bone turnover, is the real marker of healthy remodeling.
Bone remodeling does not begin the moment implant surgery ends. It develops in stages, starting with the body’s initial healing response and continuing for years afterward.
Placing a dental implant requires creating a small opening in the jawbone, called an osteotomy, to seat the implant. This initial surgical step triggers a local healing response at the site, including early bone remodeling activity, as the body works to stabilize the area around the new implant.
During osseointegration, bone cells form a direct structural connection with the implant surface. This connection creates the foundation of implant stability. Once osseointegration is complete, the bone does not stop adapting. Its focus simply shifts from initial healing to long-term maintenance, which is the process explored throughout the rest of this article.
Once an implant is restored with a crown and put into daily use, chewing introduces repeated mechanical loading, sometimes described as chewing forces or bite pressure. Bone responds to how force is applied to it, a concept sometimes called mechanotransduction. In plain terms, the bone senses pressure from biting and adjusts its structure accordingly. This is why implant biomechanics, not just implant material, plays a lasting role in how well bone supports an implant over time.
When remodeling stays balanced, it becomes one of the strongest allies of dental implant durability rather than a risk to manage.
Everyday chewing places controlled, physiological loading on the bone around an implant. Within normal ranges, this loading actually supports healthy bone density rather than wearing it down, similar to how regular activity supports bone strength elsewhere in the body.
Bone around the implant threads and near the crestal region, the area closest to the gumline, provides the physical support that keeps an implant functioning like a natural tooth. Stable remodeling in this area helps maintain that support year after year.
Patients sometimes assume that implant material alone determines how long a dental implant treatment will last. In implant dentistry, several other factors work together to determine whether permanent teeth implants continue functioning well for decades:
No single factor works alone. This is one reason a dental implant surgeon evaluates the whole picture during treatment planning, not just the implant itself.
Where and how an implant is placed has a direct effect on how force reaches the surrounding bone, which in turn affects how that bone remodels over time.
Force applied straight down the length of an implant, called axial loading, tends to distribute stress evenly through the surrounding bone. Force applied at an angle, called lateral loading, concentrates stress unevenly and can place more demand on specific areas of bone.
When an implant is angled in a way that does not align well with normal bite forces, it can create what is known as a bending moment, essentially a twisting or tipping stress at the bone-implant interface. Over time, this uneven stress, sometimes described as implant overload, can contribute to localized bone strain or prosthetic complications.
Precise three-dimensional placement, accounting for depth, angle, and spacing, helps protect the bone and soft tissue that support an implant long-term. This is explained in more detail in the practice’s article on why implant position matters more than implant size, which covers how positioning decisions affect outcomes beyond the surgery itself.
Crestal bone refers to the bone at the top, or cervical, portion of the implant, closest to the gumline. It plays an outsized role in how an implant looks and functions.
Some minor change in crestal bone level during the first year after implant placement is a normal part of healing and initial remodeling. A small amount of change does not mean an implant is failing.
Bone loss that continues to progress beyond the expected healing window is a different situation. This kind of change should be evaluated by a dental professional rather than assumed to be routine.
The gingiva, or gum tissue, surrounding an implant acts as a protective barrier for the crestal bone underneath. Consistent plaque control and management of any inflammation in this peri-implant tissue help preserve that protection over the long term.
Distinguishing normal biological adaptation from bone loss that needs attention is one of the most useful things a patient can understand about long-term implant care.
| Normal Bone Remodeling | Problematic Bone Loss |
|---|---|
| Controlled and self-limiting | Progressive over time |
| Stable once initial healing completes | Continues to worsen on imaging |
| Adaptive to chewing forces | Often linked to inflammation or mechanical overload |
| No bleeding, swelling, or mobility | May involve bleeding, discomfort, or looseness |
Normal remodeling stabilizes after the initial healing period. Bone levels level off, and the implant continues to function without ongoing decline.
According to research on bone remodeling after functional loading, bone loss that continues progressively on x-rays, especially alongside bleeding, inflammation, or discomfort, is generally considered outside the normal range for healthy remodeling. These signs warrant a professional evaluation.
A dental implant that has properly integrated with the bone should not move. Any degree of implant mobility is a different clinical situation from the small, stable bone changes that occur during normal remodeling, and it should be assessed promptly.
Because bone responds to mechanical loading, the way a patient bites and chews has a lasting effect on the bone supporting their implant.
Bone tends to strengthen in response to consistent, moderate loading and can weaken with too little use. Around dental implants, normal chewing provides that beneficial loading, helping maintain bone density in the area.
Habits like bruxism, or teeth grinding, and clenching introduce forces well beyond normal chewing. An uneven bite or a poorly designed restoration can also concentrate stress unevenly. Over time, these factors can increase mechanical stress on the bone around an implant.
Treatments involving multiple implants, such as All-on-4 implant-supported dentures, depend on distributing bite forces evenly across all the implants involved. When forces are unevenly distributed, particularly with cantilevered sections that extend beyond the last implant, certain areas of bone can experience more load than others. Balanced distribution helps protect the bone supporting the entire arch.
Not all jawbone behaves the same way, and understanding these differences helps explain why treatment planning is so individualized.
Bone contains a dense outer layer called cortical bone and a spongier inner layer called trabecular bone. The proportion of each varies by location and by patient, which affects how quickly and how predictably bone remodels around an implant.
The lower jaw, or mandible, tends to have denser bone than the upper jaw, or maxilla. This difference influences healing timelines and remodeling patterns, which is one reason treatment plans differ between upper and lower implant sites.
When a patient has experienced significant bone loss, standard implant placement may not be possible without additional planning.
In these cases, bone grafting can rebuild a foundation for implant placement, or full-arch planning may be adjusted to work around the available bone. In cases of severe upper-jaw bone loss, zygomatic implants may offer an alternative that anchors into denser bone elsewhere in the skull.
Bone grafting is often described simply as “adding bone,” but the biological reality is more involved than that.
Graft material functions as a scaffold. It gives the body’s own bone-forming cells a structure to build on, rather than simply filling space.
Grafted bone does not reach its final strength immediately. It continues to remodel and mature over a period of months as the body gradually replaces the graft framework with the patient’s own living bone.
The quality and maturity of grafted bone directly affects how well it will support an implant later on. This is one reason bone grafting is planned carefully and given adequate healing time before implant placement, rather than treated as a quick preliminary step.
Daily habits and overall health influence how well bone continues to support an implant for years after treatment.
Plaque buildup around an implant can lead to inflammation of the surrounding soft tissue. This inflammation can range from mild irritation limited to the gum tissue to more advanced inflammation that progresses to affect the supporting bone, which is why consistent plaque control matters well beyond the healing period.
Smoking reduces blood flow to oral tissues, which can affect how well bone heals and maintains itself around an implant. Patients who smoke may face a higher likelihood of complications affecting long-term bone support.
Routine clinical exams and dental imaging allow a dental team to track implant stability, bone levels, soft tissue health, and bite function over time. Catching small changes early makes them far easier to manage than waiting until a problem becomes noticeable to the patient.
Yes. Bone remains biologically active for the rest of a patient’s life, and several factors continue to influence it long after an implant has healed.
Bone metabolism naturally shifts with age, which can affect the pace and pattern of remodeling around an existing implant, even one that has functioned well for years.
Tooth loss elsewhere in the mouth, orthodontic changes, or wear on natural teeth can all alter how bite forces reach an implant, which can in turn affect how the surrounding bone responds.
Because bone continues to change in response to age, overall health, loading, and daily oral hygiene, long-term maintenance is not optional extra care. It is part of how implants remain successful for decades rather than years.
The core biology of remodeling stays the same across treatment types, but the way it plays out differs depending on how many implants are involved and how they share the workload.
A single implant carries localized forces directly at one site, which makes precise positioning especially important for that individual area of bone.
When several implants work together, load distribution becomes a shared responsibility across all of them, which can reduce the mechanical burden on any one implant site.
Full mouth dental implants rely on multiple implants working in coordination to support an entire arch. This category includes implant overdentures and All-on-4 dental implants, both of which depend on how evenly the prosthesis distributes force across all supporting implants.
Zygomatic implants anchor into the cheekbone rather than the upper jaw itself, offering an option for patients with severe upper-jaw bone loss. The bone in this region also undergoes its own remodeling process, following the same underlying biology as other implant sites even though the anchoring location differs.
Yes. Jawbone remains living tissue and continues to remodel throughout life in response to chewing forces, overall health, inflammation, and other biological factors.
Limited remodeling can occur during healing and adaptation. Progressive or excessive bone loss is a different situation and should be evaluated by a dental professional.
Yes. During osseointegration, new bone forms around the implant surface. That bone continues to remodel and adapt after integration is complete.
Excessive or poorly distributed bite forces can contribute to mechanical stress around an implant, particularly when combined with other risk factors like inflammation or bone quality issues.
Yes. Implant angulation, depth, spacing, and restorative position all influence how forces are distributed through the surrounding bone.
When a patient does not have adequate bone at the implant site, appropriately planned bone grafting can create a stronger foundation for implant placement and long-term support.
Clinical examination combined with dental imaging allows an oral surgeon to evaluate implant stability, surrounding bone levels, soft tissue health, and how these factors change over time.
Long-term dental implant success depends on more than the surgery itself. It depends on adequate bone, precise implant positioning, healthy healing, balanced bite forces, and consistent monitoring over the years that follow.
The Oral Surgery Group works with patients throughout Bucks County, Montgomery County, Doylestown, Meadowbrook, and the greater Philadelphia region to plan implant treatment with this long-term biology in mind, not just the initial procedure.
If you are considering dental implants or want to understand how your jawbone health may affect a future treatment plan, schedule a consultation to talk with our team about building a durable, well-supported implant plan from the start.


I had 2 molars removed (17 & 18) and didn’t feel a thing! Before I knew it, they were out! If I ever need oral surgery again there is no one else I will see. I would HIGHLY recommend him!
My doctor was great and the staff were great also. I would definitely recommend them to anyone. They were all very friendly and helpful.
I was able to get scheduled very soon after I first called in. And once I arrived at the office, the entire process from start to finish was prompt, professional, and expertly done. I am happy to recommend this practice to anyone.
Absolutely! I felt very confident with him. I will always return to him for any future dental work I need done. The whole experience was very well organized. I didn’t think a doctor and staff as good as this existed.
Dr. Dachowski is an amazing oral surgeon who is an expert in his field. I have had several implants placed by him and was a painless procedure. His entire team is professional and extremely concerned about their patients comfort and excellent care.
I traveled from Wilmington, DE because Dr. Dachowski and his staff are the best for teeth extractions and implants!
I am very happy with Dr. Dachowski and all of his staff. They have taken a displeasurable situation and made it the best it could be. My wife is also a patient and recommended me. I am very glad to have found them and would highly recommend them. As a business owner I understand the value of great customer service. Keep up the good work.
They are a very professional and impressive organization that uses the latest technology to do the job perfectly. They also take time to answer any questions you might have about the procedure. Will use them again and recommend them to others.
I highly recommend this practice for their quality service, knowledge & professionalism!